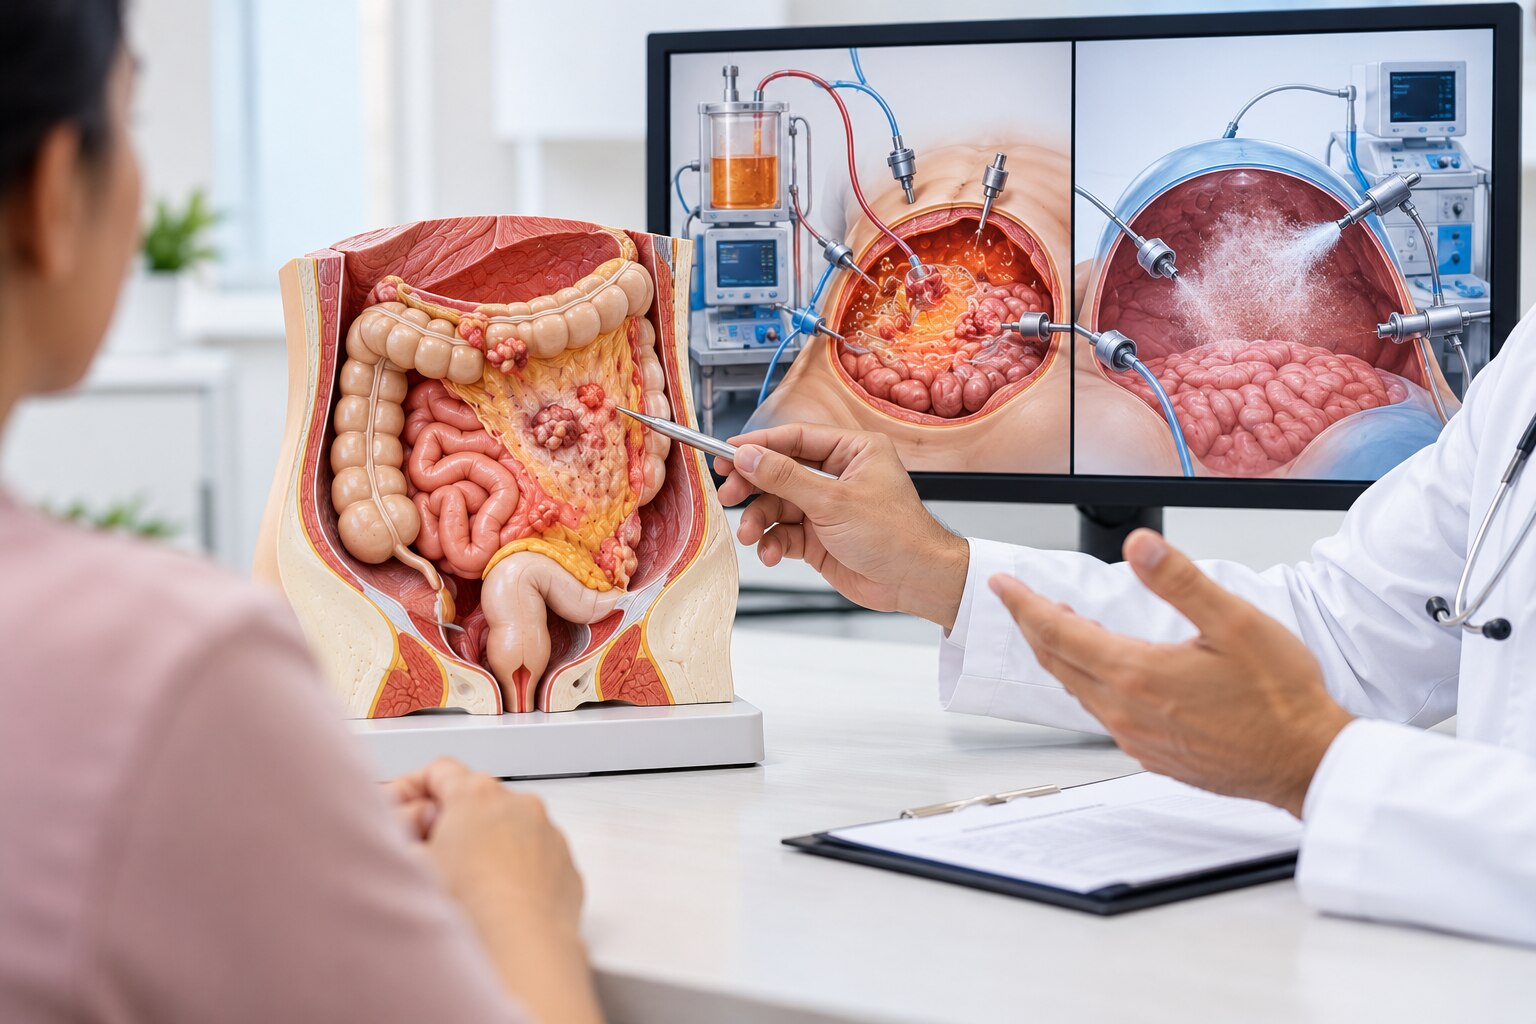
HIPEC and PIPAC are not interchangeable treatments: one combines tumour-removal surgery with heated chemotherapy, while the other delivers pressurized aerosol chemotherapy through repeated laparoscopic procedures. Your choice depends on tumour distribution, whether complete removal is realistic, your fitness for major surgery, treatment goals, and the experience and infrastructure of the Mumbai team reviewing your case.
Key takeaways
- HIPEC follows tumour-removing surgery; PIPAC delivers chemotherapy through laparoscopy.
- CRS-HIPEC requires disease that surgeons can remove completely or nearly completely.
- PIPAC may fit unresectable or recurrent peritoneal disease when surgery is unsuitable.
- Verify specialist experience, multidisciplinary review, facility capability and treatment details.
HIPEC and PIPAC solve different treatment problems
HIPEC and PIPAC address different treatment problems. HIPEC is delivered during cytoreductive surgery: the surgeon removes visible peritoneal tumour, then circulates temperature-controlled chemotherapy through the abdomen. The goal is potentially durable control or lower recurrence risk after complete or near-complete cytoreduction.
PIPAC uses laparoscopic access, a closed-abdomen aerosol system, and pressurized chemotherapy. It does not attempt the same degree of tumour removal.
| Procedure | Technical approach | Clinical role |
|---|---|---|
| HIPEC | Tumour removal followed by heated chemotherapy circulation | Selected disease that can undergo near-complete cytoreduction |
| PIPAC | Repeated laparoscopy with pressurized chemotherapy aerosol | Unresectable or recurrent disease, progression after systemic treatment, symptom control, or possible later conversion to surgery |
Drug choice, perfusion temperature, aerosol pressure, and treatment schedule depend on the tumour type and oncology team’s protocol. Neither technique suits every cancer, and PIPAC is not a proven replacement for potentially curative cytoreduction and HIPEC.
The usual pathway includes imaging and pathology review, systemic chemotherapy when indicated, multidisciplinary assessment, and diagnostic laparoscopy when scans cannot establish disease extent. The team then recommends CRS-HIPEC or serial PIPAC sessions based on tumour distribution, treatment response, organ fitness, and the realistic goal.
Searching hipec or pipac which is suitable in mumbai cannot replace that assessment.
When does a patient qualify for CRS-HIPEC?
CRS-HIPEC fits only when the team expects to remove all or nearly all visible peritoneal tumour and you can tolerate a long, complex operation. The assessment asks:
- What is the primary cancer, and does its biology respond to this approach?
- What is the peritoneal cancer index (PCI), and where are the implants?
- How extensively does disease involve the small-bowel surface or mesentery?
- Is complete or near-complete cytoreduction technically possible?
- Is disease outside the abdomen absent, or controlled well enough to proceed?
- Are your heart, lungs, kidneys, liver, blood counts, and performance status adequate for major surgery?
Selected appendiceal cancers, pseudomyxoma peritonei, colorectal peritoneal metastases, and peritoneal mesothelioma are commonly assessed. Gastric cancer and other primaries require tighter selection based on tumour biology, distribution, and the centre’s protocol.
For ovarian cancer, cisplatin HIPEC has evidence in a specifically selected interval-surgery setting after neoadjuvant chemotherapy; it is not a universal treatment for ovarian cancer or recurrent disease.
Extensive small-bowel disease, distant metastases, poor functional status, or untreated major illness can make CRS-HIPEC inappropriate. The operation also carries risks including ileus, infection, bleeding, bowel leaks or obstruction, kidney injury, low blood counts, clots, intensive-care treatment, reoperation, and prolonged admission.
A “HIPEC specialist in Mumbai” should document experience with your cancer type, PCI assessment, cytoreduction, and postoperative intensive care—not just use the title.
When is PIPAC a better-fitting strategy?
PIPAC is considered for patients with unresectable or borderline-resectable peritoneal metastases, recurrent disease, progression despite systemic therapy, or symptoms such as ascites and pain that need local control. They must also be fit enough for repeated laparoscopic procedures.
| Option | Typical fit | Main aim |
|---|---|---|
| PIPAC | Unresectable, recurrent, or symptomatic disease | Slow progression, relieve symptoms, or enable later surgery |
| CRS-HIPEC | Disease that can be removed completely or nearly completely | Potentially durable control or reduced recurrence risk |
PIPAC is not a low-risk injection or a proven replacement for potentially curative cytoreduction and HIPEC. Each session involves general anaesthesia, laparoscopic access, a chemotherapy-specific closed-abdomen aerosol system, and operating-room precautions against occupational exposure. The team monitors for bleeding, infection, bowel injury, postoperative pain, and anaesthetic complications.
Expect a series of procedures, not one definitive operation. The interval and number depend on tumour response, tolerance, organ function, and the centre’s protocol. Possible aims include:
- Slowing peritoneal progression
- Reducing ascites or other symptoms
- Preserving quality of life
- Creating a chance for later surgery
Repeated anaesthesia adds burden, while adhesions from prior procedures can complicate future operations. Before arranging pipac treatment in mumbai, ask whether it is offered within a clinical trial. PIPAC evidence, drug protocols, availability, and trial access remain less standardized than CRS-HIPEC.
How do tests and treatment goals determine the choice?
A treatment recommendation begins with a multidisciplinary review, not a procedure name. The team checks original pathology and immunohistochemistry, contrast CT of the chest, abdomen, and pelvis, prior chemotherapy records, operative reports, tumour markers in context, functional status, and kidney, liver, and blood-count assessments. Systemic therapy may come before reassessment.
CT can miss tiny peritoneal implants, confluent disease, and the true extent of tumour on the small-bowel serosa. A normal scan or one tumour-marker result cannot establish HIPEC suitability.
The peritoneal cancer index (PCI) maps tumour burden across 13 abdominal regions; diagnostic laparoscopy, or open exploration, can confirm the PCI and whether complete or near-complete removal is feasible.
| Option | Treatment sequence and burden | What the review must establish |
|---|---|---|
| CRS-HIPEC | One major operation, heated chemotherapy, and substantial recovery | Potentially removable disease, adequate fitness, and manageable disease outside the abdomen |
| PIPAC | Shorter laparoscopic admissions, but repeated treatments under general anaesthesia | Unresectable or symptomatic disease suitable for serial local control |
| Other care | Systemic therapy, conventional surgery, or symptom-focused treatment | A safer goal when neither procedure offers worthwhile benefit |
Potentially removable disease and fitness may support CRS-HIPEC. Unresectable or symptomatic disease may support serial PIPAC, particularly after systemic treatment has failed or needs local reinforcement.
For anyone asking “hipec or pipac which is suitable in mumbai,” the answer depends on PCI, tumour biology, organ reserve, symptoms, and the achievable goal—not geography or a single test.
What should you verify before choosing a Mumbai centre?
A suitable Mumbai centre can show its experience, safeguards, and results—not just advertise HIPEC or PIPAC. Ask for the actual operating hospital, treating surgeon, active PIPAC programme, and postoperative follow-up location.
| What to verify | Evidence to request | Warning sign |
|---|---|---|
| Team experience | Annual CRS-HIPEC and PIPAC numbers, by primary cancer | “Specialist” title without case volume |
| Treatment selection | PCI records, complete-cytoreduction rates, tumour types treated | No documented disease-selection criteria |
| Outcomes | Major-complication rate, mortality rate, readmissions | Only testimonials or success claims |
| Safety systems | Drug protocols, aerosol-containment procedure, ICU backup, renal monitoring, blood-bank access | Vague answers about emergencies |
Use this checklist during consultation:
- Ask whether pathology and immunohistochemistry, scans, prior chemotherapy, and operative reports are reviewed in a multidisciplinary meeting.
- Ask which primary cancers the team treats, and whether your cancer is included in its published or audited experience.
- Ask how PCI and complete cytoreduction are recorded, not merely whether they are “assessed.”
- Ask for the expected admission, recovery period, repeat PIPAC schedule, major risks, and criteria for stopping treatment.
- Ask where postoperative reviews, wound care, kidney tests, and complication management will occur.
Cercano Surgical Oncology can begin a hipec pipac consultation near girgaon through cancer-focused surgical assessment, but confirm the operating hospital and programme. Searches for peritoneal cancer procedures in opera house or a hipec specialist in mumbai identify geography, not suitability. Request a written recommendation stating the treatment goal, alternatives, evidence, admission needs, and risks.
Related service
HIPEC/PIPAC procedures Advanced Targeted Treatment for Peritoneal Surface Malignancies HIPEC (Hyperthermic Intraperitoneal Chemotherapy) and PIPAC (Pressurized... View service → |
Frequently asked questions
When does a patient qualify for CRS-HIPEC?
Eligibility depends on tumour origin, spread across the peritoneum, overall health and whether surgeons can remove visible disease completely or nearly completely.
When is PIPAC a better-fitting strategy?
PIPAC can fit patients with peritoneal disease that cannot be removed safely or completely, particularly when the treatment goal is disease control and symptom management.
How do tests and treatment goals determine the choice?
Contrast-enhanced CT or MRI, pathology, tumour distribution, prior treatments and surgical assessment help define whether the goal is durable control, recurrence reduction or palliation.
What should you verify before choosing a Mumbai centre?
Ask about the surgeon’s peritoneal malignancy experience, multidisciplinary review, anaesthesia and intensive-care support, chemotherapy protocols, complication monitoring and follow-up plan.
Keywords